
Quick answer: GLP-1 peptides are engineered analogues of glucagon-like peptide-1, a gut hormone whose native form has a plasma half-life of roughly 1.5 minutes after intravenous dosing [1]. Chemists rebuilt it to last days, producing a class that now includes five FDA-approved injectable medicines plus an oral semaglutide tablet [2][4][5][6][7][8][9]. The best evidence here is human RCT evidence, and it is unusually deep for a peptide class — but so is the documented risk profile, including a boxed warning based on animal tumor findings [2][4].
This guide is the hub for our weight-management cluster. It maps the whole incretin class, separates approved drugs from investigational ones, and routes you to the individual compound pages. If you are new to peptides generally, start with our plain-English introduction first.
What “GLP-1 peptides” actually means
The phrase covers three overlapping things. First, the native hormone: GLP-1 itself, released from the gut after eating. Second, the approved drug class — peptide analogues of GLP-1 engineered for long duration. Third, a broader group of multi-receptor peptides that hit GLP-1 plus GIP, glucagon or amylin receptors. Only the second group has FDA-approved members.
The biology: GLP-1, GIP and glucagon receptors
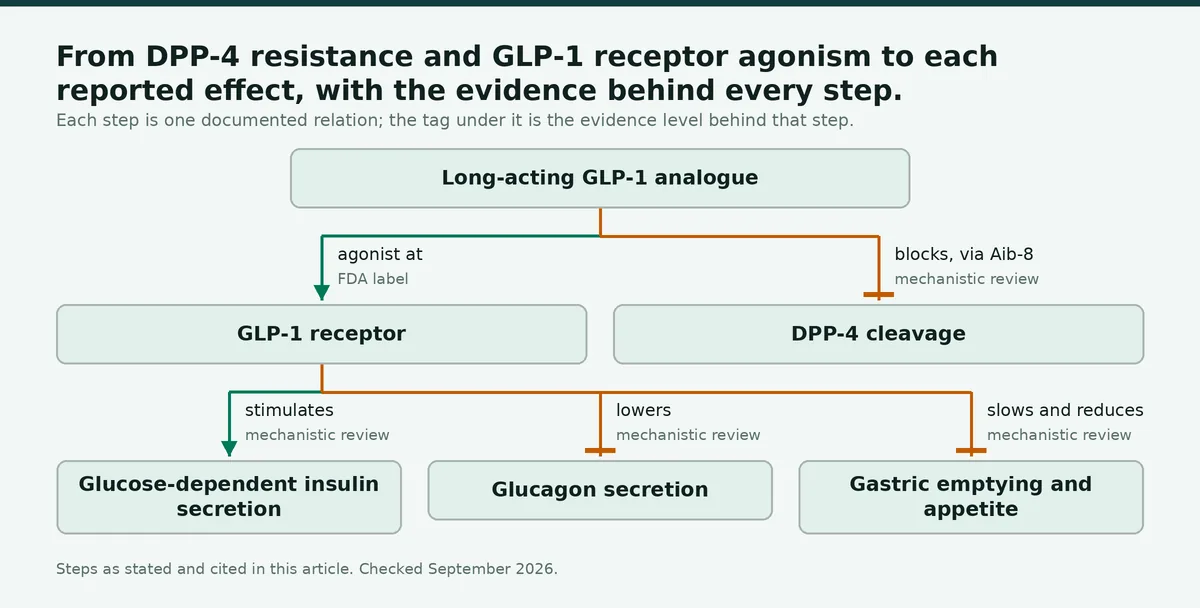
| Step | Relation | Target | Evidence |
|---|---|---|---|
| Long-acting GLP-1 analogue | agonist at | GLP-1 receptor | FDA label [2][4] |
| Long-acting GLP-1 analogue | blocks, via Aib-8 | DPP-4 cleavage | mechanistic review [1] |
| GLP-1 receptor | stimulates | Glucose-dependent insulin secretion | mechanistic review [1] |
| GLP-1 receptor | lowers | Glucagon secretion | mechanistic review [1] |
| GLP-1 receptor | slows and reduces | Gastric emptying and appetite | mechanistic review [1] |
GLP-1 is an incretin — a hormone released in response to nutrients that amplifies insulin release. It stimulates glucose-dependent insulin secretion, lowers glucagon secretion in a glucose-dependent way, slows gastric emptying, and reduces appetite [1]. The effect is substantial: GLP-1 and its partner hormone account for a large share of the insulin released after a meal [1].
GIP (glucose-dependent insulinotropic polypeptide) is the second incretin. Tirzepatide activates both the GIP and GLP-1 receptors, and its FDA label describes it as a dual agonist that enhances insulin secretion and reduces glucagon in a glucose-dependent manner [4][5].
The glucagon receptor is the third pathway in play. Glucagon raises hepatic glucose output but also increases energy expenditure, which is why several investigational peptides deliberately add glucagon receptor activity to a GLP-1 backbone [11].
Why native GLP-1 had to be redesigned
Native GLP-1 is useless as a drug in unmodified form. Its half-life is roughly 1.5 minutes after intravenous dosing and about 1.5 hours after subcutaneous dosing in humans, because the enzyme dipeptidyl peptidase-IV (DPP-4) clips its N-terminus [1].
Three engineering moves fixed this, and they define the class. Substituting an unnatural amino acid (Aib) at position 8 blocks DPP-4 cleavage. Attaching a fatty acid — palmitate for liraglutide, a C18 di-acid for semaglutide — lets the peptide bind reversibly to albumin, which shields it from clearance. Linker chemistry then restores receptor potency that the fatty acid would otherwise cost [1]. That programme combined in vitro receptor-potency screening with animal pharmacokinetics; in mini-pigs, semaglutide showed a half-life of about 75 hours after subcutaneous dosing [1].
The payoff shows up on the human labels: liraglutide’s elimination half-life is approximately 13 hours, dulaglutide’s about 5 days, and semaglutide’s about 1 week [6][7][2].
Class map: approved versus investigational
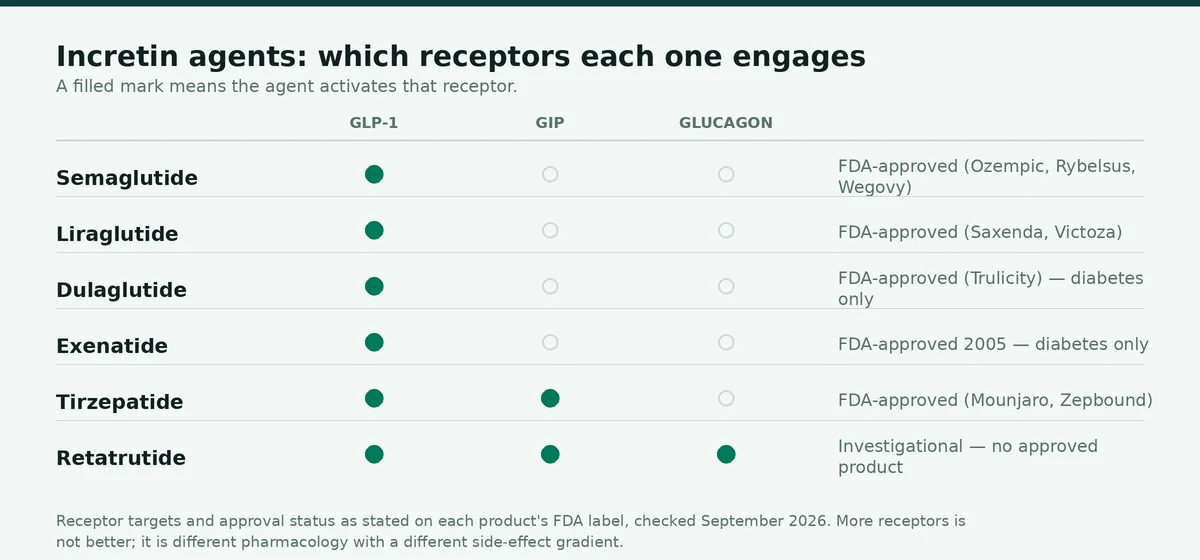
Regulatory status below was checked September 2026 against FDA labels and approval letters.
FDA-approved agents
| Agent | Receptor targets | Route / frequency | US status (checked September 2026) |
|---|---|---|---|
| Semaglutide (Wegovy) | GLP-1 | Subcutaneous, weekly; tablets also approved | Approved — weight reduction, CV risk reduction, and noncirrhotic MASH with F2–F3 fibrosis under accelerated approval [2] |
| Semaglutide, oral | GLP-1 | Oral tablet | Approved; the Rybelsus R2 tablet formulation was renamed Ozempic tablets on 30 Jan 2026 [9] |
| Tirzepatide (Zepbound) | GIP + GLP-1 | Subcutaneous, weekly | Approved — weight reduction and moderate-to-severe obstructive sleep apnea in adults with obesity [4] |
| Tirzepatide (Mounjaro) | GIP + GLP-1 | Subcutaneous, weekly | Approved — glycemic control in type 2 diabetes and CV risk reduction [5] |
| Liraglutide (Saxenda) | GLP-1 | Subcutaneous, daily | Approved — weight reduction in adults and patients aged 12+ [6] |
| Dulaglutide (Trulicity) | GLP-1 | Subcutaneous, weekly | Approved — type 2 diabetes and CV risk reduction; not approved for weight management [7] |
| Exenatide (Byetta) | GLP-1 | Subcutaneous, twice daily | Approved 2005 — type 2 diabetes only; no boxed warning on this label [8] |
Exenatide is the class ancestor. Its label notes the peptide was originally identified in the lizard Heloderma suspectum, and its terminal half-life is about 2.4 hours [8].
Investigational agents
| Agent | Receptor targets | Stage reported | US status (checked September 2026) |
|---|---|---|---|
| Retatrutide | GIP + GLP-1 + glucagon | Phase 3 (TRIUMPH programme) | Investigational; sponsor-reported topline only [10][11] |
| CagriSema (cagrilintide + semaglutide) | Amylin/calcitonin + GLP-1 | Phase 3 | Investigational [11] |
| Cagrilintide (alone) | Amylin + calcitonin | Phase 2 | Investigational [11] |
| Survodutide | GLP-1 + glucagon | Phase 2 reported | Investigational [11] |
| Mazdutide | GLP-1 + glucagon | Phase 3 | Investigational in the US [11] |
We found no FDA-approved product containing retatrutide, cagrilintide, survodutide or mazdutide when we checked in September 2026. Amylin analogues such as cagrilintide are an adjacent class rather than incretins — they act at amylin and calcitonin receptors, and the peer-reviewed pipeline literature describes their appeal as combination partners rather than standalone agents [11].
What the human evidence actually shows
Semaglutide: the STEP programme
In the pivotal 68-week trial in adults with obesity or overweight without type 2 diabetes (STEP 1, roughly 1,961 randomized), the FDA label reports a least-squares mean weight change of −14.9% with semaglutide 2.4 mg versus −2.4% with placebo — a treatment difference of −12.4% (95% CI −13.3 to −11.6) [3]. In that trial, 83.5% versus 31.1% lost at least 5% of body weight, 66.1% versus 12.0% lost at least 10%, and 47.9% versus 4.8% lost at least 15% [3]. Human RCT.
The companion trial in adults with type 2 diabetes produced smaller numbers: −9.6% versus −3.4%, a difference of −6.2% [3]. Human RCT. That gap between diabetic and non-diabetic populations is consistent across the class and worth remembering when comparing headline percentages.
Tirzepatide: SURPASS and SURMOUNT
The Zepbound label reports the 72-week obesity trial (SURMOUNT-1) as −15.0% at 5 mg, −19.5% at 10 mg and −20.9% at 15 mg, versus −3.1% for placebo [4]. Human RCT.
The SURPASS programme supported the type 2 diabetes approval under the Mounjaro brand, including a trial comparing tirzepatide against semaglutide 1 mg in people with type 2 diabetes [5]. Human RCT. We have not quoted per-dose SURPASS figures here because we could not verify them cleanly against the label tables; that detail belongs on the tirzepatide compound page.
Cardiovascular outcomes: SELECT
SELECT randomized 17,604 adults with established cardiovascular disease and obesity or overweight, without diabetes. Major adverse cardiovascular events occurred in 569 of 8,803 people on semaglutide 2.4 mg versus 701 of 8,801 on placebo — 6.5% versus 8.0%, hazard ratio 0.80 (95% CI 0.72–0.90) [2]. All-cause mortality HR was 0.81 (0.71–0.93) and myocardial infarction HR 0.72 (0.61–0.85); the stroke component did not reach significance individually, HR 0.89 (0.72–1.11) [2]. Human RCT. This trial is why an obesity drug now carries a cardiovascular indication on its label.
Retatrutide: phase 2, then TRIUMPH-1
Retatrutide adds glucagon receptor activity to the GIP/GLP-1 combination. A peer-reviewed pipeline review summarizes its 48-week phase 2 obesity trial as producing mean weight loss of 24.2% at the 12 mg dose versus 2.1% with placebo [11]. Human RCT.
Phase 3 followed. On 21 May 2026 Eli Lilly reported topline results from TRIUMPH-1 (NCT05929066), an 80-week trial in 2,339 participants. Using the efficacy estimand, mean weight reduction was −19.0% at 4 mg, −25.9% at 9 mg and −28.3% at 12 mg, versus −2.2% for placebo; under the more conservative treatment-regimen estimand the figures were −17.6%, −23.7% and −25.0% versus −3.9% [10]. Human RCT.
Two caveats matter. These are sponsor-reported topline results, not a peer-reviewed publication — Lilly stated that detailed results would be presented at future meetings and published later [10]. And the gastrointestinal burden scaled with dose: nausea was reported in 28.6%, 38.4% and 42.4% of participants versus 14.8% on placebo, with similar gradients for diarrhea and constipation [10]. Full detail sits on the retatrutide page.
The rest of the pipeline
The same pipeline review reports a 46-week phase 2 trial of survodutide with mean weight loss of 18.7% at 4.8 mg versus 2.0% for placebo; a 48-week phase 3 mazdutide trial with 12.6% mean weight loss versus a 0.5% gain on placebo; cagrilintide monotherapy at roughly 10.8% over 26 weeks; and CagriSema phase 3 results of 22.7% in obesity without diabetes and 13.7% with diabetes [11]. Human RCT in each case, but read them as single-source summaries until the individual papers are on the table — we treat them that way on the cagrilintide, survodutide and mazdutide pages.
Side effects and risks
This section deserves at least as much attention as the efficacy numbers, and the labels are the best source for it.
Gastrointestinal effects dominate. Nausea, diarrhea, vomiting, constipation, abdominal pain, dyspepsia and eructation all appear among the most common adverse reactions (≥5%) on both the semaglutide and tirzepatide labels [2][4]. In TRIUMPH-1, nausea affected more than four in ten participants at the top retatrutide dose [10].
Gallbladder events. The Wegovy label reports increased cholelithiasis and cholecystitis: 1.6% versus 0.7% for cholelithiasis and 0.6% versus 0.2% for cholecystitis in adults, with higher rates in pediatric patients [2]. Acute gallbladder disease also carries a warning on the tirzepatide label [4].
Pancreatitis signal. Both labels warn that acute pancreatitis — including fatal and non-fatal hemorrhagic or necrotizing forms — has been observed with GLP-1 receptor agonists, and instruct that the drug be discontinued if pancreatitis is suspected [2][4].
Thyroid C-cell tumors — the boxed warning. This is an animal finding carried onto human labels. Semaglutide “causes thyroid C-cell tumors at clinically relevant exposures” in rodents, tirzepatide does so in rats, and liraglutide does so in both sexes of rats and mice; each label states it is unknown whether the drug causes such tumors, including medullary thyroid carcinoma, in humans, and each contraindicates use in people with a personal or family history of MTC or MEN 2 syndrome [2][4][6]. Notably, the exenatide label carries no boxed warning [8].
Muscle and lean mass. A 2026 systematic review and meta-analysis of 7 RCTs in 821 patients found absolute lean mass fell by 1.74 kg (95% CI −3.04 to −0.45) and by 3.06% from baseline, while lean mass as a proportion of total body mass rose by 1.81% [12]. The authors estimate roughly 30% of total weight lost corresponds to lean mass, varying by agent [12]. Human RCT (pooled). Whether that matters functionally is still an open question, not a settled one.
Stopping treatment. A retrospective observational cohort of 4,182 patients across a federated health-record network found that in the six months after a last semaglutide or tirzepatide prescription, about two-thirds had stable weight or continued losing; among those who did regain, average regain reached roughly 4% within four months [13]. Human observational. Real-world regain patterns look more varied than the “it all comes back” framing suggests, but this is EHR data, not a randomized withdrawal trial.
Compounded and “research use only” incretins
This is where the peptide market and the pharmacy market collide, and the FDA has been explicit.
As of 31 May 2026 the agency had received 990 adverse event reports for compounded semaglutide and more than 730 for compounded tirzepatide, while noting that state-licensed pharmacies are not required to report, so the true count is likely higher [14]. FDA also states that compounded drugs are not FDA approved and have not been reviewed for safety, effectiveness or quality before marketing [14].
On salt forms — the sodium and acetate salts that circulate in grey-market supply — FDA says it is “not aware of any lawful basis for their use in compounding” [14].
Most relevant to this site’s readers: FDA has called out companies illegally marketing products “falsely labeled ‘for research purposes’ or ‘not for human consumption’” while selling them to consumers with dosing instructions [14]. A research-use-only label does not make a product lawful for human use. It is a marketing device, and the agency treats it as one.
Dosing errors are a documented, concrete harm. A 2024 FDA alert described patients receiving five to twenty times the intended dose of compounded semaglutide from multiple-dose vials, and healthcare providers miscalculating by five to ten times when converting units — with outcomes including nausea, vomiting, fainting, dehydration, acute pancreatitis, gallstones and hospitalization [15]. FDA has since launched a “Green List” import-screening system for GLP-1 active ingredients, detaining APIs from facilities it has not inspected or cleared [16], and in February 2026 announced it would use “all available compliance and enforcement tools” against mass-marketed non-approved compounded GLP-1 products [17].
For the legal framing in more depth, see our guide to peptide legal status and research vs compounded vs FDA-approved peptides. If you are assessing supplier documentation, our COA guide explains what a certificate of analysis can and cannot tell you.
WADA status
Checked September 2026: we did not find GLP-1 receptor agonists named as prohibited substances in WADA’s 2026 Prohibited List, which took effect 1 January 2026 [18]. WADA has instead included semaglutide in its Monitoring Program since 2024 and has funded work to build detection methods for several GLP-1 analogues in blood and dried blood spot samples [19]. Monitoring is a surveillance mechanism, so athletes in tested sport should treat this as a status that can change and check the current List and their own sport’s rules directly.
How these compare
Within the approved group, the practical split is receptor coverage and duration. Semaglutide is a single-receptor GLP-1 agonist with a roughly weekly half-life [2]; tirzepatide adds GIP [4]; liraglutide is a daily GLP-1 agonist with a 13-hour half-life [6]; exenatide is short-acting and twice-daily [8]. Head-to-head detail lives in semaglutide vs tirzepatide.
Within the investigational group, the differentiator is whether glucagon or amylin activity is added on top. Retatrutide is the triple agonist [10][11]; CagriSema pairs an amylin analogue with semaglutide [11]. We compare the two leading candidates in tirzepatide vs retatrutide.
We score every compound on the same axes — duration of action, target selectivity and evidence depth — using our published comparison framework. On evidence depth this class is the outlier among peptides: the approved incretins sit at the top of the scale because they have regulatory review, published phase 3 trials and outcome data behind them, while the investigational agents sit several rungs lower despite impressive weight-loss percentages. The semaglutide and tirzepatide pages carry the full scoring.
FAQ
Are GLP-1 peptides the same as the prescription drugs?
Only some of them. Semaglutide, tirzepatide, liraglutide, dulaglutide and exenatide are FDA-approved prescription medicines with defined indications and labels [2][4][5][6][7][8]. Retatrutide, survodutide, mazdutide and cagrilintide are investigational compounds; we found no FDA-approved product containing them as of September 2026 [11].
What is the difference between a GLP-1 agonist and a dual or triple agonist?
A GLP-1 agonist activates one receptor. Tirzepatide activates the GIP receptor as well [4], and retatrutide adds the glucagon receptor to make a triple agonist [10][11]. More receptors is not automatically better — it is different pharmacology with a different, and in retatrutide’s case dose-dependent, side-effect gradient [10].
Why does the label carry a thyroid cancer boxed warning?
Because rodents given these drugs developed thyroid C-cell tumors at clinically relevant exposures. The labels state plainly that it is unknown whether the same happens in humans, and contraindicate use in people with a personal or family history of medullary thyroid carcinoma or MEN 2 [2][4][6]. That is an animal finding driving a human precaution, not a demonstrated human outcome.
Do people regain weight after stopping?
Some do. In a retrospective observational cohort of 4,182 patients, about two-thirds had stable or continued weight loss in the six months after their last prescription, while roughly a third regained — averaging about 4% within four months [13]. Human observational. That is a weaker design than a randomized withdrawal trial, so treat it as indicative.
Is “research use only” semaglutide legal to use?
No — the label does not change what the product is. FDA has specifically flagged companies marketing GLP-1 products “falsely labeled ‘for research purposes’ or ‘not for human consumption’” while selling them to consumers, and treats them as unapproved drugs of unknown quality [14].
Are GLP-1 peptides banned in sport?
We did not find them named as prohibited in WADA’s 2026 Prohibited List [18]. Semaglutide has been in WADA’s Monitoring Program since 2024, with active work on detection methods [19]. Athletes should verify current status directly rather than rely on a static page.
References
- Knudsen LB, Lau J. The Discovery and Development of Liraglutide and Semaglutide. Frontiers in Endocrinology. 2019. https://www.frontiersin.org/journals/endocrinology/articles/10.3389/fendo.2019.00155/full
- WEGOVY (semaglutide) injection and tablets — Highlights of Prescribing Information. US Food and Drug Administration. 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/215256s033lbl.pdf
- WEGOVY (semaglutide) injection — Prescribing Information, Section 14 Clinical Studies. US Food and Drug Administration. 2023. https://www.accessdata.fda.gov/drugsatfda_docs/label/2023/215256s007lbl.pdf
- ZEPBOUND (tirzepatide) injection — Highlights of Prescribing Information. US Food and Drug Administration. 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/217806s042lbl.pdf
- MOUNJARO (tirzepatide) injection — Label. DailyMed, US National Library of Medicine. 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d2d7da5d-ad07-4228-955f-cf7e355c8cc0
- SAXENDA (liraglutide) injection — Highlights of Prescribing Information. US Food and Drug Administration. 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/206321s025lbl.pdf
- TRULICITY (dulaglutide) injection — Label. DailyMed, US National Library of Medicine. 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=463050bd-2b1c-40f5-b3c3-0a04bb433309
- BYETTA (exenatide) injection — Label. DailyMed, US National Library of Medicine. 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=53d03c03-ebf7-418d-88a8-533eabd2ee4f
- NDA 213051/S-030 Supplement Approval Letter (semaglutide tablets). US Food and Drug Administration. 2026. https://www.accessdata.fda.gov/drugsatfda_docs/appletter/2026/213051Orig1s030ltr.pdf
- Lilly’s triple agonist, retatrutide, delivered powerful weight loss in pivotal Phase 3 obesity trial (TRIUMPH-1 topline). Eli Lilly and Company. 2026. https://investor.lilly.com/news-releases/news-release-details/lillys-triple-agonist-retatrutide-delivered-powerful-weight-loss
- Park C, Kim Y, Raygani S, Grunvald E. A glimpse into the pipeline of anti-obesity medication development: combining multiple receptor pathways. Frontiers in Endocrinology. 2025. https://www.frontiersin.org/journals/endocrinology/articles/10.3389/fendo.2025.1630199/full
- Laverde LP et al. Effect of GLP-1 receptor agonists at doses for obesity management on muscle health: systematic review and meta-analysis of randomized controlled trials. International Journal of Obesity. 2026. https://www.nature.com/articles/s41366-026-02118-y
- Murugadoss K et al. Weight trajectories after last tirzepatide or semaglutide prescription across a federated health network. Biology Methods and Protocols. 2026. https://academic.oup.com/biomethods/article/11/1/bpag020/8659581
- FDA’s Concerns with Unapproved GLP-1 Drugs Used for Weight Loss. US Food and Drug Administration. 2026. https://www.fda.gov/drugs/drug-alerts-and-statements/fdas-concerns-unapproved-glp-1-drugs-used-weight-loss
- FDA alerts health care providers, compounders and patients of dosing errors associated with compounded injectable semaglutide products. US Food and Drug Administration. 2024. https://www.fda.gov/drugs/human-drug-compounding/fda-alerts-health-care-providers-compounders-and-patients-dosing-errors-associated-compounded
- FDA Launches Green List to Protect Americans from Illegal Imported GLP-1 Drug Ingredients. US Food and Drug Administration. 2025. https://www.fda.gov/news-events/press-announcements/fda-launches-green-list-protect-americans-illegal-imported-glp-1-drug-ingredients
- FDA Intends to Take Action Against Non-FDA-Approved GLP-1 Drugs. US Food and Drug Administration. 2026. https://www.fda.gov/news-events/press-announcements/fda-intends-take-action-against-non-fda-approved-glp-1-drugs
- 2026 Prohibited List. World Anti-Doping Agency. 2025 (in force 1 January 2026). https://www.wada-ama.org/en/resources/2026-prohibited-list
- Analysis of GLP-1 receptor agonists (Semaglutide, Liraglutide etc.) in blood. World Anti-Doping Agency, Scientific Research. 2024. https://www.wada-ama.org/en/resources/scientific-research/analysis-glp-1-receptor-agonists-semaglutide-liraglutide-etc-blood